Evaluation of a patient with suspected prosthetic heart valve malfunction should begin with a careful history and physical examination. Before suspecting malfunction. It IS important that the clinician be aware of the normal auscultatory findings in patients with prosthetic valves. Depending on the type and location of a prosthesis, varying auscultatory findings may be encountered. The intensity of the opening and closing clicks, their character or associated murmurs. or both, will depend on the type of prosthetic valve. the heart rate and rhythm and the underlying hemodynamic status.
The average rate of prosthetic valve dysfunction ranges between 10 and 30% at 10 years. Early detection of valve dysfunction is thus crucial to successfully manage these complications.
The dysfunction of the BMV was induced by restricting the motion of one or both leaflets to represent the most possible prosthetic valve dysfunction scenarios. For the dysfunctional BMVs cases, the normal valve opening area was reduced by 25 and 50% to represent mild and moderate-to-severe valve dysfunction, respectively. These two grades of dysfunction were achieved by
restricting the opening angle of one leaflet by 50 and 100%, respectively . The additional scenarios with impairment of the opening of both leaflets are : (i) 25% restriction in the opening angle of both leaflets (i.e. 25% reduction in valve opening area: mild dysfunction); (ii) 50% restriction in the opening angle of both leaflets (i.e. 50% reduction in valve opening area: moderate-to severe dysfunction).

Images of BMV with normal and abnormal functions. This figure shows the maximum opening during ejection for normal and dysfunctional BMV: (A) In vitro study: high-speed camera images. (B) In vivo study: cinefluoroscopic images.(European Heart Journal – Cardiovascular Imaging (2014) 15, 142–151)

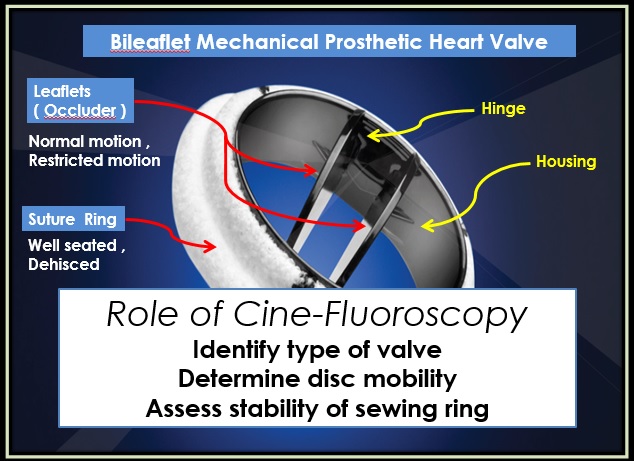
However , Doppler velocity index (DVI) is proven to be highly sensitive in detection of moderate to severe mechanical valve dysfunction but cinefluroscopy allows for the identification of patients with “Doppler silent” PVT ( prosthetic valve thrombosis ) , even to identify pseuroresponders to guide duration of lytic treatment and to predict effect of thrombolysis .
The average rate of prosthetic valve dysfunction ranges between 10 and 30% at 10 years. Early detection of valve dysfunction is thus crucial to successfully manage these complications.

The dysfunction of the BMV was induced by restricting the motion of one or both leaflets to represent the most possible prosthetic valve dysfunction scenarios. For the dysfunctional BMVs cases, the normal valve opening area was reduced by 25 and 50% to represent mild and moderate-to-severe valve dysfunction, respectively. These two grades of dysfunction were achieved by
restricting the opening angle of one leaflet by 50 and 100%, respectively . The additional scenarios with impairment of the opening of both leaflets are : (i) 25% restriction in the opening angle of both leaflets (i.e. 25% reduction in valve opening area: mild dysfunction); (ii) 50% restriction in the opening angle of both leaflets (i.e. 50% reduction in valve opening area: moderate-to severe dysfunction).

Images of BMV with normal and abnormal functions. This figure shows the maximum opening during ejection for normal and dysfunctional BMV: (A) In vitro study: high-speed camera images. (B) In vivo study: cinefluoroscopic images.(European Heart Journal – Cardiovascular Imaging (2014) 15, 142–151)

However , Doppler velocity index (DVI) is proven to be highly sensitive in detection of moderate to severe mechanical valve dysfunction but cinefluroscopy allows for the identification of patients with “Doppler silent” PVT ( prosthetic valve thrombosis ) , even to identify pseuroresponders to guide duration of lytic treatment and to predict effect of thrombolysis .


